AI in Medicine (2026): What Happened to the 'Medical Revolution' and What Works Now
In 2022, this page ran under the title “Artificial intelligence is shaping a new medical revolution”. It was built on four stories: an AI called BioMind beating 15 senior doctors in a Beijing contest, a University of Exeter model predicting dementia two years ahead, AI thermal cameras screening for fever during the COVID-19 pandemic, and a French professor training doctors to use these tools. This update checks what happened to each of those narratives, then covers where AI in medicine has real, peer-reviewed evidence by 2026. We look at predicting disease before symptoms, precision medicine, surgery, and daily use by doctors. To ground this in current capability, we also tested an open AI model on 1,273 US medical licensing exam questions. For imaging trials, AI diagnosis versus doctors and the best-known failures, see our separate guide to AI in healthcare.
The 2022 claims at a glance
| 2022 story | What it claimed | What we found in 2026 |
|---|---|---|
| BioMind vs 15 doctors (2018) | AI beat senior doctors at brain tumor diagnosis | Contest figures from press reports only, never peer-reviewed; the company later co-authored about 13 research papers |
| Exeter dementia model (2021) | Predicts dementia two years ahead | 92% accuracy but 45% sensitivity: it missed more than half of new cases |
| AI fever cameras (2020) | Safer, contactless COVID screening | Temperature screening missed 77-100% of infections in a Cochrane review |
| Training doctors in AI (2021) | Doctors need AI courses | Nice’s 112-hour diploma still runs; US and Canadian schools teaching AI rose from 88 to 140 |
The 2022 headlines, four years later
BioMind vs 15 doctors
The contest figures for BioMind come strictly from press reports. According to those reports, on June 30, 2018, the AI system correctly diagnosed brain tumors on 225 cases with 87% accuracy, compared to 66% for 15 senior doctors. It also predicted hematoma expansion with 83% accuracy versus 63% for the physicians. The AI took about 15 minutes; the doctors took 30. Wang Yongjun, executive vice president of Beijing Tiantan Hospital, stated the contest was meant to help doctors get used to AI, not to pit humans against machines. The contest itself was never published as a peer-reviewed study. No paper reporting those specific 87% vs. 66% figures was found.
What came after is more modest, but it is peer-reviewed. Beijing’s “BioMind Technology” appears as an author affiliation on about 13 PubMed papers from 2021 to 2024. In one 2021 study on predicting the growth of brain bleeds, deep learning on non-contrast CT used 1,899 images for training and 1,117 for validation, achieving an AUC of 0.778–0.780. On a 118-patient clinical set, sensitivity was 89.3% and specificity 77.8%. Another 2022 paper in Radiology: AI reported 96% accuracy in telling spinal cord tumors from demyelinating lesions, on a prospective test cohort of 157 patients. We found no record of approval for BioMind by China’s medical device regulator, the NMPA.
The Exeter dementia model
The University of Exeter model published in JAMA Network Open in December 2021 used data from 15,307 participants without dementia at baseline, collected from US memory clinics between 2005 and 2015. The headline figure was 92% accuracy. But accuracy sits alongside a sensitivity of 0.45. This means the model missed more than half of the people who went on to develop dementia. High accuracy here mostly reflects that 90% of patients stayed dementia-free. The model drew on 258 variables, yet a version with only six still reached 91% accuracy. It flagged up to 84% of people whose initial dementia diagnosis was later reversed, suggesting possible misdiagnosis.
A Cambridge follow-up in 2024 used cognitive tests and MRI to predict progression from mild cognitive impairment to Alzheimer’s. That model achieved 81.66% accuracy, an AUC of 0.84, sensitivity of 82.38%, and specificity of 80.94%, validated on real-world data from several countries.
AI fever cameras
Remark Holdings repurposed its China “smart school” platform into AI thermal kits and reported $1.1 million in thermal-imaging revenue in the US in Q2 2020. But the science was weak. A Cochrane rapid review in September 2020 found that temperature screening alone had a sensitivity of 0.00–0.23, meaning it missed roughly 77 to 100 of every 100 infected people. In a safety communication on March 4, 2021, the FDA said, as reported by trade press, that thermal imaging systems are “not effective” at diagnosing COVID-19 and should not be used to screen many people at once, and it sent warning letters to four companies over unapproved systems.
Training doctors to use AI
Prof. Olivier Humbert launched the “Diplôme universitaire Intelligence Artificielle et Santé” at Université Côte d’Azur in August 2021. The first cohort ran from November 2021 to April 2022. The program is 112 hours long, mixing remote courses and in-person practicals for doctors, pharmacists, and biomedical engineers. Humbert, a professor of nuclear medicine, described AI as “an incredible opportunity” for doctors rather than a threat, and the university’s course page still lists him as its contact. In North America, the Association of American Medical Colleges (AAMC) reported that the number of medical schools teaching AI in curricula grew from 88 in 2023 to 140 in 2024.
Predicting disease before symptoms
Predicting disease before symptoms is where AI in medicine has moved from lab curiosities to deployed systems. The Kaiser Permanente Advance Alert Monitor (AAM) deployed across 19 hospitals between 2016 and 2019 covered 548,838 non-ICU hospitalizations. Alerts flagged a 12-hour risk of deterioration. For a score of 5, the risk was ≥8%. Nurses monitored remotely and called rapid-response teams. In this observational design, 30-day mortality after an alert had an adjusted relative risk of 0.84. The authors estimated that about 520 deaths were avoided per year.
Sepsis prediction with TREWS, published in Nature Medicine in 2022, monitored 590,736 patients across five hospitals. For 6,877 sepsis patients flagged before antibiotics, if a clinician confirmed the alert within three hours, in-hospital mortality fell by 3.3 percentage points. In high-risk patients, the absolute reduction was 4.5 percentage points. This was a prospective cohort, not randomized.
The Mayo Clinic AI-ECG for low ejection fraction (EAGLE) trial was a pragmatic cluster-randomized trial involving 120 primary-care teams and 22,641 adults. New low-EF diagnoses within 90 days were 2.1% in the AI group versus 1.6% in the control. Among AI-positive patients, the rate was 19.5% versus 14.5%. Overall echo use was similar. RETFound, a foundation model trained self-supervised on 1.6 million unlabelled retinal images, outperformed comparison models on eye disease and predicting systemic disorders like heart failure with fewer labeled data.
Sybil, developed at MIT and MGH, predicts future lung cancer risk from one low-dose CT scan, using no clinical data or radiologist annotation. It achieved a 1-year AUC (a 0-to-1 measure of how well a model separates cases from non-cases) of 0.92 on the US National Lung Screening Trial scans, 0.86 at Massachusetts General Hospital and 0.94 at Chang Gung Memorial Hospital in Taiwan. The model is open source.
For Alzheimer’s, the FDA cleared the first blood test in May 2025 (Fujirebio Lumipulse G), but this is not AI. The p-tau217 clocks from WashU are statistical models, not deep learning. They predicted age at symptom onset with a median absolute error of 3.0–3.7 years. The dementia prediction story is now about biomarkers plus models.
Delphi-2M, published in Nature in September 2025, is a modified GPT architecture trained on 0.4 million UK Biobank participants and validated on 1.9 million Danish individuals. It predicts the rates of more than 1,000 diseases with accuracy comparable to existing single-disease models. It can generate synthetic health trajectories up to 20 years ahead. The authors noted it also learned biases from training data.
Precision medicine: treatment for the individual patient
Precision medicine uses AI to tailor treatment to the individual patient. AlphaMissense, published in Science in 2023, classifies 89% of missense variants as either likely benign or likely pathogenic. DeepMind states there are 71 million possible missense variants. Breakdown: 57% likely benign, 32% likely pathogenic, 11% uncertain. Only 0.1% of the 71 million had been confirmed by human experts.
Paige Prostate received FDA authorization in September 2021 as the first AI pathology tool. According to the FDA’s announcement as reprinted by trade press, the study it reviewed involved 16 pathologists and 527 slides. Detection improved by 7.3%, with 70% fewer false negatives and 24% fewer false positives. The impact on final patient diagnosis was not evaluated.
According to the company, ArteraAI’s prostate test is included in NCCN Guidelines for prostate cancer (2024) as category 2A, Level IB evidence. It is described as the first AI tool in national guidelines for both prognosis and prediction, helping personalize therapy. It uses multimodal AI on H&E biopsy slide images plus clinical data.
Robots in the operating room
The idea of a robot performing surgery entirely on its own sounds like science fiction, but the reality of autonomous surgical robotics is far more nuanced. To understand where the technology actually stands, we have to look at the difference between research prototypes and what is currently cleared for human use. A systematic review published in npj Digital Medicine in 2024 analyzed 49 FDA-cleared surgical robots. The data shows that 86% operate at Level 1, meaning they are tools that extend the surgeon’s movements. Only 6% reached Level 3, which allows for conditional autonomy where the robot can perform specific tasks without continuous human control. None of the 49 systems achieved Level 5, or full autonomy, where the robot would handle an entire procedure without human intervention.
This gap between lab experiments and clinical reality is illustrated by two prominent research systems. In 2022, the Smart Tissue Autonomous Robot (STAR) demonstrated autonomous laparoscopic small-bowel anastomosis in pigs. The study, published in Science Robotics, reported that the robot outperformed expert human surgeons in consistency and accuracy regarding suture spacing and leak pressure. The pigs survived for one week post-operation, proving the technical feasibility of the procedure. However, this was an in vivo study in an animal model, not a human clinical trial.
A follow-up system, SRT-H, published in Science Robotics in July 2025, took a different approach using language-conditioned imitation learning. The system performed cholecystectomy steps on eight ex vivo gallbladders with a 100% success rate. According to press reports, the procedure was split into 17 tasks, such as identifying ducts and clipping arteries, and the robot was slower than human surgeons. Crucially, this was an ex vivo study on organs removed from pigs, not an operation on a living patient.
Neither STAR nor SRT-H is currently FDA-cleared for human use. They remain research systems. The current landscape of AI in medicine in the operating room is defined by assistance, not replacement. In cleared systems the surgeon, not the robot, decides when to cut or stitch. Until a system can navigate the variable anatomy of a live human patient and handle complications autonomously, the surgeon remains firmly in command.
Can AI pass a medical exam?
Passing a medical licensing exam is a significant milestone, but it is not the same as practicing medicine. Large language models have shown remarkable ability to answer medical board questions, leading to headlines about AI doctors. However, the data reveals a complex picture of capability versus competence.
In 2023, Kung et al. tested ChatGPT on 350 questions from the June 2022 USMLE sample exam. When indeterminate answers were censored, ChatGPT scored 75.0% on Step 1, 61.5% on Step 2CK, and 68.8% on Step 3. The passing threshold is approximately 60%. When indeterminate answers were counted as wrong, the scores dropped significantly to 45.4%, 54.1%, and 61.5%, respectively. This was a sample set, not a real-time exam sitting, but it demonstrated that a general-purpose model could reach passing levels on multiple steps.
Earlier benchmarks were much lower. The MedQA dataset, released in 2020, contained 12,723 English medical exam questions. The best baseline model at the time achieved only 36.7% accuracy. By 2025, Med-PaLM 2 reached 86.5% on the MedQA dataset, a significant leap. Physicians preferred Med-PaLM 2’s answers on several axes, and in a pilot study, specialists preferred its responses over generalist physicians 65% of the time.
By April 2026, performance on MedQA had saturated. The Vals.ai leaderboard, archived on April 16, 2026, shows leading models like o1 scoring 96.52%, GPT-5.1 at 96.38%, and Gemini 3.1 Pro Preview at 96.37%. Vals said that because performance had “saturated”, it no longer runs the benchmark on new models.
Why does this matter? Because answering a multiple-choice question is not the same as diagnosing a patient. An exam question has a single correct answer derived from a static prompt. A patient presents with messy, overlapping symptoms, comorbidities, and social factors. Passing the USMLE proves an AI can retrieve and synthesize medical knowledge, but it does not prove it can manage the uncertainty of clinical practice.
Our test: an open AI model on 1,273 medical exam questions
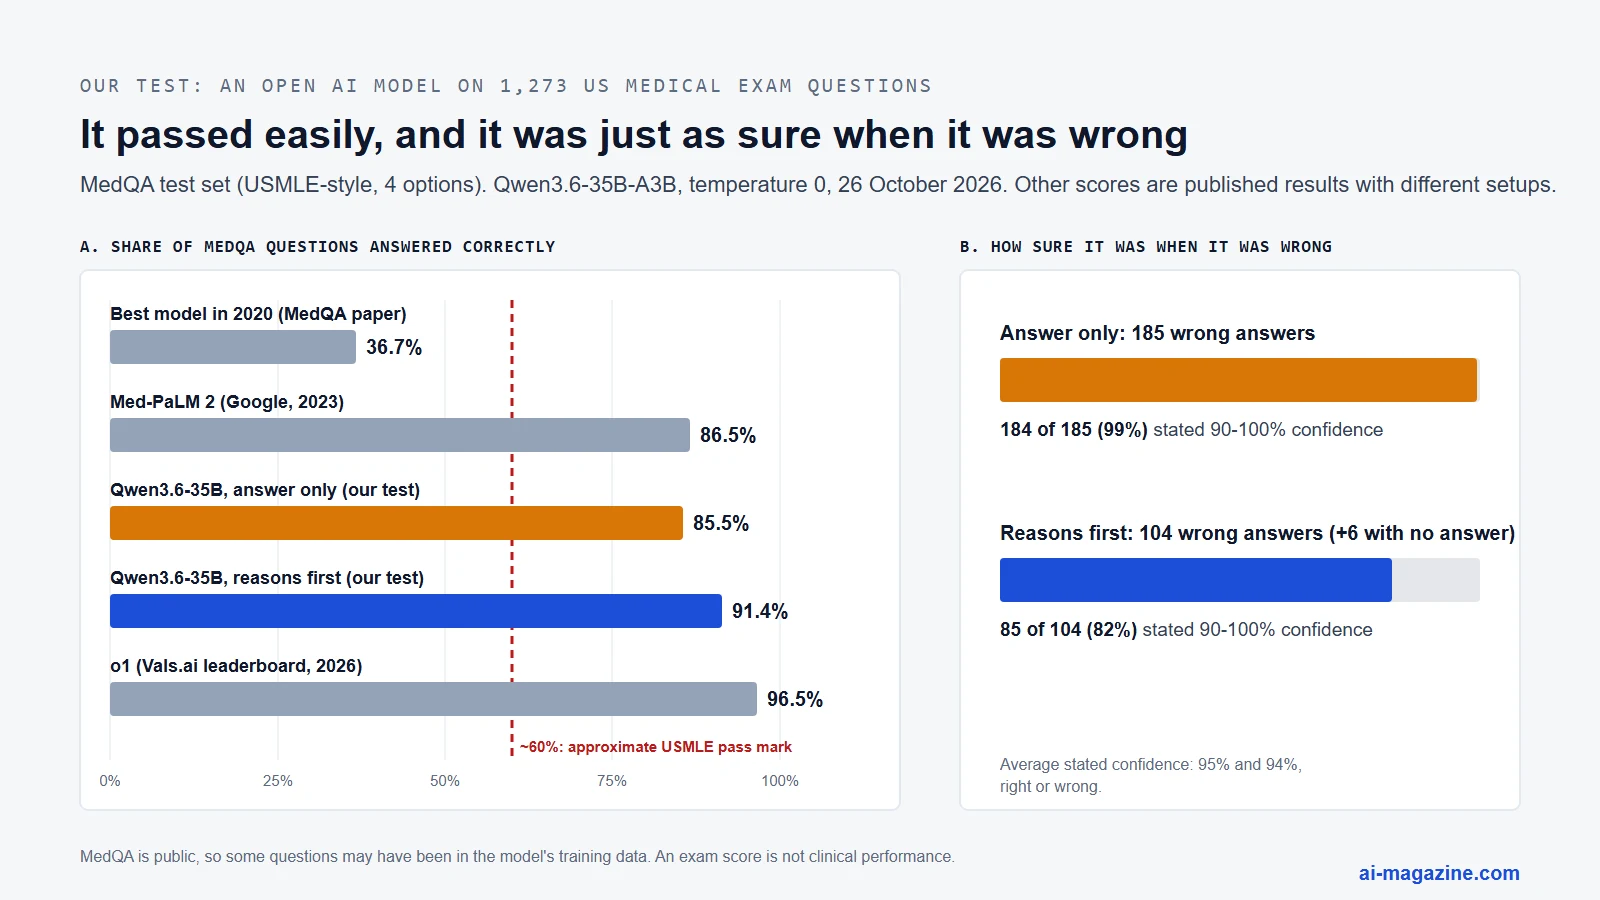
Exam scores are usually reported for the biggest commercial models. We wanted to see what a mid-sized open model that anyone can download does today, and whether it knows when it is wrong. On 26 October 2026 we gave all 1,273 questions of the MedQA test set (USMLE-style, four answer options) to Qwen3.6-35B-A3B, an open-weight model from Alibaba’s Qwen team (we ran a community build compressed to 4-bit precision on our own server), at temperature 0. We asked twice:
- Answer only: reply with the letter and a confidence from 0 to 100.
- Reasons first: think step by step in up to 150 words, then give the letter and the confidence.
| Answer only | Reasons first | |
|---|---|---|
| Correct answers (of 1,273) | 1,088 (85.5%) | 1,163 (91.4%) |
| Step 1 questions (679) | 85.6% | 92.8% |
| Step 2 and 3 questions (594) | 85.4% | 89.7% |
| Average stated confidence | 95% | 94% |
| Wrong answers stated with 90-100% confidence | 184 of 185 | 85 of 104 (+6 with no answer) |
It passed with room to spare. A model small enough to run on a single server scored 85.5% without explanation and 91.4% when it reasoned first, far above the roughly 60% pass mark and in the range Google’s specialised Med-PaLM 2 reached in 2023. In 2020 the best system managed 36.7% on the same kind of questions. Asking for reasons first fixed 6 percentage points of errors, more on the basic-science Step 1 questions than on the clinical Step 2 and 3 ones.
Its confidence was almost useless. Answering directly, the model said it was at least 90% sure in 1,271 of 1,273 answers, including 184 of its 185 wrong ones. With reasoning, confidence carried a little signal: answers stated at 90% or more were right 93% of the time, answers at 80-89% only 70% of the time. Still, 85 wrong answers came with 90% or higher confidence. In a clinic, a wrong answer delivered with the same certainty as a right one is the dangerous kind.
What this means: passing a licensing exam is no longer evidence that a model is special, and a high score says nothing about whether it will flag its own mistakes. That is why the studies above that measure patient outcomes, like the Kaiser and TREWS alert systems, matter more than exam results.
Limits: one model, one run at temperature 0, multiple-choice questions only, no images. MedQA has been public since 2020, so some questions may have appeared in the model’s training data. Six reasoning answers ran out of length and gave no letter even with a larger limit; we counted them as wrong.
How doctors use AI today
The hype cycle has moved past the initial novelty phase into practical adoption. According to the American Medical Association’s 2026 survey on augmented intelligence, as reported in medical trade press, conducted from January 15 to February 2, 2026, 81% of physicians now use AI professionally, up from just 38% in 2023. The survey of 1,692 physicians found that doctors average 2.3 AI use cases, compared to 1.1 in 2023. The top uses are summarizing research and clinical documentation, tasks that eat into administrative time.
Hospitals are adopting predictive AI at a rapid pace. A September 2025 data brief from ASTP, the US health IT office formerly known as ONC, analyzed trends in predictive AI use across non-federal acute care hospitals. In 2024, 71% of hospitals used EHR-integrated predictive AI, an increase from 66% in 2023. Adoption is heavily skewed toward larger, system-affiliated institutions: 86% of system-affiliated hospitals use predictive AI compared to only 37% of independent hospitals. Urban hospitals lead at 81% adoption, while rural hospitals trail at 56%.
The fastest-growing use cases are not diagnostic. Billing and scheduling AI grew by 25 percentage points and 16 percentage points, respectively. Treatment recommendations, which often grab headlines, grew by only 2 percentage points. This suggests hospitals are prioritizing administrative efficiency over clinical decision support for now.

Medical education is also catching up. An AAMC data snapshot from June 2025 reported that 140 U.S. and Canadian medical schools had AI in their curriculum in 2024, up from 88 in 2023. Of those, 107 schools included AI in their required curriculum, up from 61. As AI in medicine becomes standard, the next generation of doctors will graduate with a baseline familiarity with these tools.
The rules for medical AI
Regulation is struggling to keep pace with the speed of development. The World Health Organization released guidance on the ethics and governance of AI for health in January 2024. The document contains over 40 recommendations covering five use areas: diagnosis and clinical care, patient-guided use, clerical tasks, education, and research. Key recommendations include assigning a specific regulator to approve health Large Multimodal Models (LMMs) and mandating independent post-deployment audits published by user subgroup.
In the United States, the FDA has been working on frameworks for AI-enabled software. In December 2024, the FDA finalized guidance on Predetermined Change Control Plans (PCCPs). This allows manufacturers to pre-authorize future updates to their AI models without submitting a new premarket review each time. However, the broader draft guidance on “Artificial Intelligence-Enabled Device Software Functions,” issued in January 2025, is still a draft. It outlines lifecycle management and marketing submission recommendations but is not yet final.
The European Union is also adjusting its timeline. Under the original AI Act, AI in medical devices covered by the MDR/IVDR was set to become high-risk from August 2, 2027. According to law firms tracking it, the Digital Omnibus regulation (Regulation (EU) 2026/1744), published in July 2026, moves this deadline to August 2, 2028. Standalone high-risk systems under Annex III move to December 2, 2027. These shifts reflect a desire to give developers more time to adapt to the new regulatory landscape.
What this means for patients
If you are a patient, here is how to navigate the growing presence of AI in your care:
- Ask whether a tool is cleared, and for what. Software that uses AI is not automatically FDA-cleared, and a clearance covers one specific use, not medicine in general.
- High accuracy can hide missed cases. A model might report 92% accuracy, but if the sensitivity is low, it is missing a significant number of true cases. Always ask about sensitivity and specificity, not just overall accuracy.
- Chatbots and exam scores are not a diagnosis. As our test below shows, a model can score over 90% on exam questions and still be fully confident when it is wrong. Do not assume a chatbot’s output is equivalent to a doctor’s diagnosis.
- Predictive alerts help only when clinicians act on them. AI can flag a risk of sepsis or deterioration, but the benefit depends on the hospital’s workflow. If the alert is ignored or the nurse is too busy to respond, the AI’s prediction is useless.
- Protect your privacy. Health data you type into a consumer chatbot may not have the protections of your medical record; check the app’s privacy terms before sharing it.
Frequently asked questions
How is AI used in medicine today? Doctors mostly use it to summarize research and write clinical notes, and 71% of US hospitals used predictive AI in 2024, increasingly for billing and scheduling. Clinical uses with the best evidence include imaging and early-warning alerts for sepsis and deterioration.
Can AI diagnose diseases better than doctors? AI can match or exceed human performance on specific, narrow tasks like reading retinal scans or detecting prostate cancer in pathology slides. However, it does not outperform doctors across the board, and a high accuracy figure can hide a low sensitivity. Our AI in healthcare guide covers the head-to-head studies.
Can AI predict diseases like dementia? Partly. The University of Exeter model reached 92% accuracy but caught only 45% of the people who developed dementia within two years. Newer models using cognitive tests and MRI show improved sensitivity, but they are still tools for risk stratification, not definitive diagnosis.
Will AI replace doctors? Unlikely in the near term. AI is better at data processing and pattern recognition. Doctors excel at contextual judgment, empathy, and handling complex, multi-system problems. The trend is toward augmentation, where AI handles the data and doctors handle the decision-making.
Are there robots that operate on their own? Research prototypes like STAR and SRT-H have performed autonomous tasks in pigs and ex vivo organs. However, no FDA-cleared system performs a whole soft-tissue operation autonomously on humans. Current surgical robots are tools controlled by surgeons.
Can ChatGPT pass the USMLE? Yes. A 2023 study found ChatGPT at or near the passing threshold on Step 1, Step 2CK, and Step 3. Newer models score above 90% on the MedQA question set, and in our own test even an open model reached 91.4%, but passing an exam is not the same as practicing medicine.
Is medical AI regulated? Yes, but the rules are evolving. The FDA has finalized guidance on change control plans for AI software but is still drafting broader lifecycle guidelines. The EU has delayed its high-risk medical device AI deadline to 2028. The WHO has issued ethical guidelines recommending independent audits and clear regulatory oversight.